

by Shilpi Aggarwal, PhD, Freelance Writer
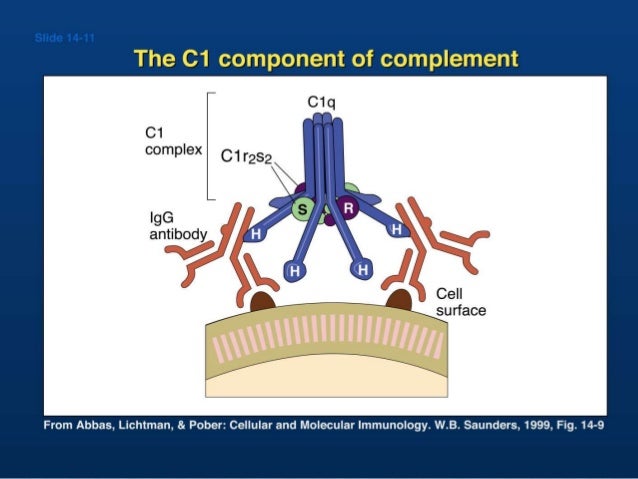
In a new research article published on April 25, 2024, in Scientific Reports, researchers have proposed the potential use of serum measurements of C1q complement as a relevant biomarker to determine plaque stability in coronary artery disease (CAD) patients and for the assessment of the disease. The open-access article is titled “The Relationship Between Complement C1q and Coronary Plaque Vulnerability Based on Optical Coherence Tomography Analysis.” This conclusion arises from a retrospective observational study done by the researchers using data on plaque morphology and C1 complement serum levels for 221 CAD patients who were admitted to The Second Affiliated Hospital of Xi’an Jiaotong University in China between April 2021 and July 2022 and underwent simultaneous coronary angiography and optical coherence tomography (OCT) evaluation. The researchers initiated this study to determine the association between complement C1q and vulnerable plaque morphology in CAD patients.
CAD is a chronic multifactorial atherosclerotic disease. It is classified into acute coronary syndrome (ACS) and chronic coronary syndrome (CCS) based on clinical symptoms, signs, and laboratory test results. The researchers divided the patients into ACS and CCS groups to study the relation of complement Cq1 with these conditions. A comparative study between the ACS and CCS groups showed that the plasma complement C1q levels were lower in ACS patients.
Further, a comparison of the OCT features for the two groups showed that the ACS group had considerably higher incidences of plaque rupture, plaque erosion, and thrombus in culprit lesions than the CCS group. Moreover, the CCS group had thicker fibrous caps for lipid plaques than the ACS group. In CAD, a thicker fibrous cap typically indicates a more stable plaque that is less prone to rupture and less likely to result in harmful events like heart attacks. Thus, it can be deduced that there is a potential difference in plaque stability between the two groups with CCS having a more stable condition for plaques.
Based on values for serum concentration of C1q complement, the patients with low C1q complement levels were more vulnerable to plaque rupture, plaque erosion, thrombus, and cholesterol crystals. The thickness of fibrous cap in lipid-rich plaques showed a strong positive correlation with serum levels of complement C1q, indicating that complement C1q could improve the stability of lipid-rich plaques. In addition, a multivariate logistic regression analysis with other confounding factors, such as age, sex, alcohol drinking, smoking, total triglyceride, low-density lipoprotein cholesterol, and apolipoprotein B showed that the complement C1q is a better predictor for plaque rupture, erosion, thrombus, and cholesterol crystals.
Based on the above-stated observations, the researchers concluded that a higher complement C1q level may decrease the incidence of ACS and increase the stability of the plaques. Furthermore, the complement C1q was seen to be a better predictor of the stability of plaques than others. Therefore, the complement C1q shows the potential to be used as a valuable biomarker for plaque vulnerability in CAD patients and also assessment of ACS and CCS conditions.